 Ampicillin Vs Amoxicillin: Key Differences Explained Chemical Differences and Mechanism of Action Compared
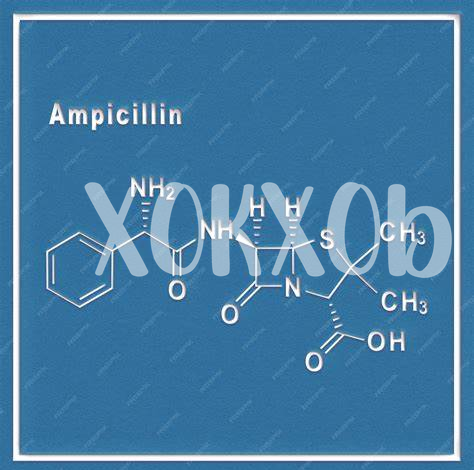
Think of the two drugs as siblings from the same blueprint: both carry the beta lactam ring that disrupts bacterial cell wall assembly by binding penicillin binding proteins and triggering lysis. Chemically they differ in side chains; amoxicillin carries a para hydroxyl group that changes its behavior. This OH increases polarity and oral absorption, giving amoxicillin higher bioavailability and predictable serum levels after oral dosing. Ampicillin is more acid labile in some formulations and required different dosing strategies, though both remain effective when delivered appropriately. Mechanistically there is no dramatic gap: both are bactericidal, time dependent killers whose success depends on maintaining concentrations above the MIC. The chemical tweak in amoxicillin translates to easier outpatient use and preferred oral therapy for susceptible infections. Clinicians weigh these chemical and pharmacokinetic distinctions when choosing route, dose, and stewardship friendly options in practice.
| Feature | Ampicillin | Amoxicillin |
|---|
| Key chemical difference | Amino side chain | Para hydroxyl on side chain |
| Oral bioavailability | Lower, more variable | Higher, more predictable |
| Common routes | IV/IM and oral | Primarily oral |
Spectrum of Activity: Which Infections Each Treats
In clinical stories, choices hinge on bugs and setting. ampicillin is notable for activity against Listeria monocytogenes, enterococci and several streptococci, making it valuable in meningitis, endocarditis and some neonatal infections when organisms are susceptible and also some intraabdominal infections. Amoxicillin usually offers similar core beta‑lactam coverage but with better oral absorption and convenience; it’s preferred for outpatient respiratory tract infections, otitis media and uncomplicated urinary tract infections caused by susceptible E. coli and H. influenzae strains and some mild skin infections. Laboratory susceptibility guides final choice: resistant organisms or beta‑lactamase producers steer clinicians toward alternatives, whereas confirmed susceptible isolates allow targeted therapy with either agent depending on site, severity and route of administration. Clinical judgment matters.
Absorption, Dosing, and Bioavailability: Real World Effects
Clinicians often recall that oral ampicillin has variable uptake, so IV use remains common in acute settings. Stories from emergency wards highlight timely IV administration when absorption is uncertain. Bioavailability influences dosing: higher oral fractions allow simpler schedules, while lower absorption demands increased dose frequency or parenteral routes. Real-world effects include missed doses, food interactions, and patient factors like age and gut motility altering blood levels. Understanding these practical differences helps tailor therapy, balancing convenience, adherence, and therapeutic targets for each patient. Shared decision making mirrors these pharmacologic realities too.
Side Effects, Allergies, and Safety Considerations Compared

Patients often notice mild gastrointestinal upset or rash when taking ampicillin, and clinicians watch for Stevens–Johnson syndrome though it is rare. Liver enzymes and blood counts may need monitoring during prolonged courses; most adverse effects are self-limiting but warrant reassessment if severe or persistent. Allergic reactions occur in penicillin-sensitive individuals; careful history and alternative agents are essential. In pregnancy and childhood, benefits are weighed against risks, and dosing adjustments are used for renal impairment. Educating patients about signs of hypersensitivity improves safety and supports prompt management and antibiotic stewardship principles.
Clinical Uses and Prescribing Trends in Practice
In everyday practice, clinicians choose antibiotics not just for pathogens but for patient context, and ampicillin often appears in stories of straightforward newborn and enterococcal infections. Its historical role anchors many empirical regimens, yet practitioners weigh its pros and cons against alternatives. Outpatient trends favor amoxicillin, but hospital teams still reserve ampicillin for specific syndromes: neonates, Listeria meningitis, and targeted enterococcal therapy when susceptibility permits. Decision-making blends microbiology, local resistance data, and patient factors like allergy or renal function. Guidelines and stewardship programs steer prescriptions toward narrow-spectrum agents when possible, promoting intravenous-to-oral switches and dose optimization. Observing these trends helps clinicians preserve efficacy while tailoring care to individual patients and local formulary and cost considerations.
| Use | Typical Setting |
|---|
| Neonatal sepsis | Inpatient |
| Listeria meningitis | Hospital |
Resistance Patterns and Laboratory Susceptibility Testing Implications
Clinical resistance to aminopenicillins has evolved unevenly; once-reliable activity against some streptococci and enterococci is undermined by beta-lactamase production and altered penicillin-binding proteins. Surveillance data now guide empiric choices more than historical practice; regional trends. Laboratories increasingly report minimum inhibitory concentrations rather than binary susceptible/resistant calls, allowing clinicians to weigh dose adjustments and combination therapy. Detection of extended-spectrum beta-lactamases or AmpC enzymes directly changes interpretation for ampicillin and related drugs. Phenotypic tests remain essential, but molecular assays that identify resistance genes speed decisions during outbreaks. Correlating genotype with phenotype helps laboratories forecast treatment failures and informs stewardship interventions aimed at preserving aminopenicillin utility in practice. Clinicians should review lab reports and local antibiograms before choosing therapy; susceptibility trends may prompt using alternatives or combining agents. Clear lab‑clinic communication shortens time to effective therapy and supports public health surveillance and stewardship. PubChem — Ampicillin StatPearls — Ampicillin (NCBI Bookshelf)
|