 Debunking Myths about Symbicort Use Common Symbicort Myths Versus Scientific Evidence
Rumors about inhalers often spread faster than facts; Symbicort’s combination therapy is supported by trials showing reduced exacerbations and improved lung function. Users worry about immediate side effects, yet studies report predictable, manageable reactions; clinicians monitor dosing to balance symptom control with minimal risk. Claims that Symbicort causes dependence misunderstand inhaler pharmacology; its corticosteroid and bronchodilator components treat inflammation and constriction without addictive properties in most patients. Finally, evidence supports proper use: adherence and correct inhaler technique maximize benefits and reduce misconceptions, so patients should consult professionals for guidance regularly.
| Myth | Evidence |
|---|
| Causes addiction | Pharmacology shows no addictive mechanism; studies report no dependence |
| Unsafe long-term | Long-term trials show benefits with monitoring; side effects manageable |
Does Symbicort Cause Dependence or Addiction

I remember worrying my inhaler might become a crutch, but clear evidence shows inhaled corticosteroids and long-acting bronchodilators like symbicort do not cause addiction. They relieve airway inflammation, not pleasure pathways. Dependence in the medical sense—needing increasing doses to control symptoms—can reflect under-treatment or disease progression rather than drug addiction. Discussing symptoms with a clinician prevents misunderstandings. Withdrawal from abruptly stopping oral steroids differs from stopping inhaled therapy; sudden oral steroid cessation can cause true physiologic withdrawal, while stopping symbicort mainly risks symptom return, not chemical dependence. Clear education, proper inhaler technique, and regular review reduce fear and promote safe use. If concerns persist, ask your healthcare team for tailored advice and reassurance and support.
Long Term Safety Steroid Concerns Explained Clearly
Many patients fear long-term steroid effects, picturing dramatic harm. Inhaled corticosteroids like symbicort produce minimal systemic exposure. Good daily control reduces need for oral steroid bursts, which pose higher overall risk to health over time. Concerns like reduced growth velocity, bone density loss, cataracts, or adrenal suppression are dose-related and uncommon at inhaled doses. Regular review and using the lowest effective symbicort dose minimize these risks while maintaining symptom control. Local effects such as oral thrush or hoarseness can occur, but simple measures reduce them: proper inhaler technique, rinsing and using spacer devices. Report persistent problems so clinicians can adjust symbicort dosing or delivery appropriately. The bottom line: benefits of controlled breathing and fewer exacerbations generally outweigh small risks when symbicort is used correctly. Regular check-ups, growth or bone monitoring when indicated, and open dialogue ensure safe long-term use periodically.
Proper Use Versus Misuse Inhaler Technique Matters
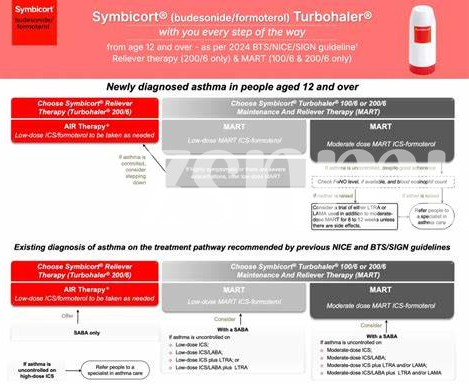
Every time I handed the inhaler to a new patient, I watched hope turn into confusion. A quick demonstration—shake, exhale, deep slow inhalation, hold for ten seconds—made symptoms fall away faster than apologies for missed doses. With symbicort, technique matters: shake well, prime if new, exhale fully then seal lips around the mouthpiece. Press as you start inhaling slowly and deeply, hold your breath ten seconds, and wait sixty seconds between puffs. Common mistakes—shallow inhalation, spraying between breaths, or skipping rinsing—reduce benefit and mimic treatment failure. Misuse can increase rescue inhaler visits, waste medication, and raise local side effects like oral thrush without simple preventive steps. Practice technique during clinic visits or with a pharmacist; ask for return demonstration. Spacers help children and encourage slow inhalation. Regularly review dose timing and inhaler condition so you get benefit and fewer flare-ups.
Symbicort during Pregnancy and Breastfeeding Safety
Pregnancy can feel like a maze of decisions, but keeping airways stable is essential for both parent and baby. Uncontrolled asthma carries clear risks such as low oxygen, preterm birth, and growth issues, so maintaining treatment often matters more than theoretical medication concerns. Many specialists support continued use of inhaled combination therapies when needed, and discuss tailoring doses to the smallest effective level while monitoring symptoms closely with regular checkups. During breastfeeding, inhaled therapies have minimal transfer into milk because systemic absorption is low; experts generally view benefits of symptom control as outweighing small exposure risks. For symbicort specifically, brief discussions with a clinician can confirm appropriate timing and technique to reduce infant exposure further. Observe the baby for unusual sleepiness or feeding changes, report concerns, and never stop prescribed inhalers suddenly without medical guidance. Shared discussions with clinicians matter.
| Trimester | Advice |
|---|
| 1–3 | Discuss risks and monitor |
When to Seek Medical Help with Symbicort
Once, a runner delayed care as symptoms worsened; increased breathlessness, persistent wheeze, or inability to complete normal activity despite using inhaler are warning signs that need prompt medical assessment to prevent severe exacerbations and hospitalization. Allergic reactions such as rash, facial swelling, hives, or sudden difficulty breathing demand immediate emergency attention; similarly, high fever, persistent cough with colored sputum, or chest pain after inhaler use warrant timely clinician review evaluation. Persistent oral thrush, hoarseness, significant mood swings, blurred vision, or unexplained weight loss should prompt discussion with your prescriber; these may signal medication side effects, need for dosing review, or alternative therapies to reduce risk. If routine rescue doses fail to relieve severe symptoms, or if dizziness, fainting, severe fatigue, or abdominal pain occur, seek immediate care. Keep an updated asthma/COPD action plan, bring inhalers, and contact your healthcare team.
|